Osteoporosis advice at Seegarten Klinik
Osteoporosis is rarely a disease of the bone; it is usually a reflection of systemic disorders.
In the osteoporosis consultation we assess your personal risk and show you how to strengthen your bones: with exercise, nutrients and, where necessary, further therapies.
The problem in osteoporosis is a loss of bone elasticity (because the calcium salts predominate) and of bone mass (because the organic bone substance, the proteins, is broken down more quickly). Under these conditions, accidents with awkward falls in old age are more likely to result in a broken bone. In advanced osteoporosis, however, even minor “traumas” such as lifting a shopping bag, bending down or merely sneezing can cause a fracture.
The consultation is intended for women and men with a diagnosis of osteoporosis, with risk factors, or with questions about an ongoing treatment.
Bring your previous bone density reports and laboratory results with you, or submit them in advance.
What bone density measurement tells us – and what it does not
Today the diagnosis of osteoporosis is usually based on bone density measurement (DEXA) and the T-score calculated from it: if it is below −2.5, the bone is considered osteoporotic.
The measurement has its limits. Density is mass per volume; DEXA, however, scans the bone in only two dimensions and measures an areal density in grams per square centimetre. Devices, reference databases and correction factors differ, and the measurement itself varies by up to 3% at the lumbar spine and up to 5% at the hip.
What DEXA does not show
- the strength of the bone
- its structure and quality
- its ability to repair itself
- its metabolism
Even under medication, bone density says little about the risk of fracture: its increase explains only 4 to 28% of the reduction in fractures (Li 2001, Cummings 2001, Sarkar 2001).
Trabecular bone score and computed tomography
The trabecular bone score (TBS) is a measure that assesses the microarchitecture of the bone. It is a quantitative (not qualitative!) assessment of bone structure based on grey-level texture analysis. The TBS is derived from the DEXA scan, so this evaluation also ignores the spatial picture. Even so, the TBS is meant to provide information on fracture risk that goes beyond the bone density measurement alone.
The diagnosis of osteoporosis has made significant progress with the introduction of volumetric computed tomography, also known as quantitative computed tomography (QCT). This state-of-the-art imaging method makes it possible to visualise the bone structure in three dimensions at high resolution and thus offers a detailed analysis of bone density. Unlike the conventional DEXA scan, which only produces a two-dimensional image, volumetric CT can capture the spatial and therefore the actual density of the bone and so give more precise indications of fragility and fracture risk.
In practice, however, QCT is rarely used to diagnose osteoporosis. The reasons are the high cost, limited availability, radiation exposure (especially with repeated measurements), the complexity of interpreting the data with specialised software, and the supposed adequacy of the DEXA scan for most clinical decisions. Finally, health insurers do not reimburse the expensive measurement. No wonder QCT remains a specialised technique for research.
The T-score does not know your weight
The T-score compares your bone density with that of healthy adults aged about 25 to 30. Disease is thus defined as distance from youth. The T-score takes account of sex, the Z-score also of age, and neither of body weight.
But bones carry weight: the heavier a person, the denser their bones. Many slim women are therefore given a diagnosis of osteoporosis although they simply have light bones for a low weight. The same is true of the muscles.
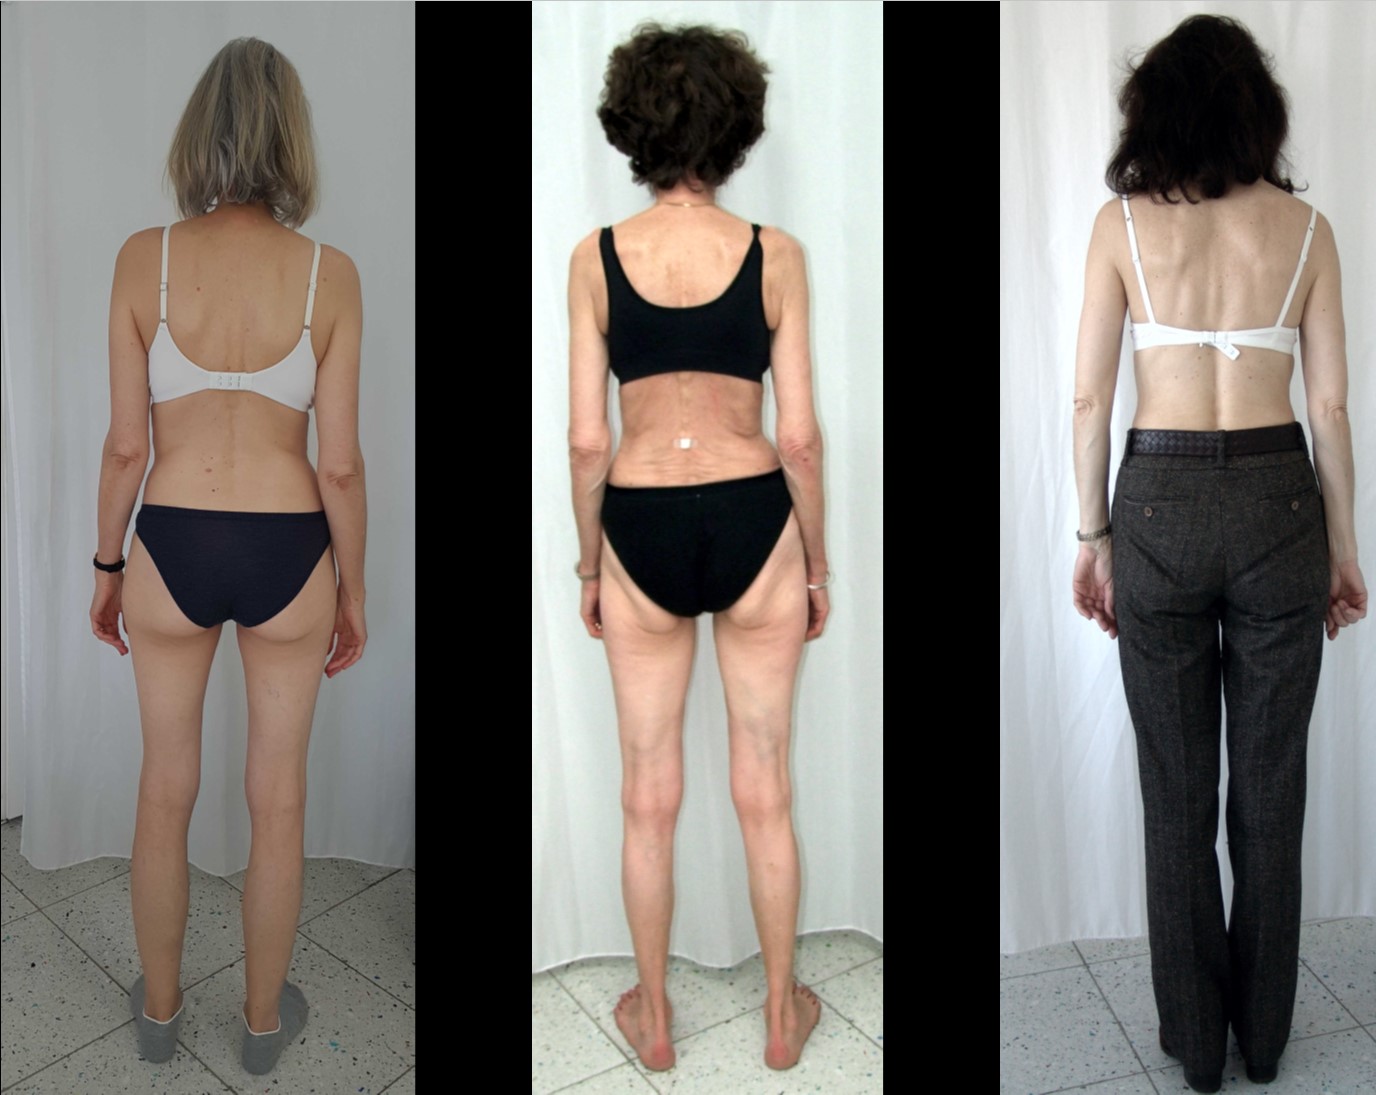
Anyone in the yellow or red area but above, on or just below the line needs no treatment. In the usual evaluation, all these people are considered osteopenic or osteoporotic and are given an osteoporosis therapy they do not need at all.
Conversely, an overweight person can have an osteoporotic constellation despite normal bone density, namely when their B-score is low. This is rare, however.
The B-score: bone density in relation to weight
The B-score (“bone score”) relates your measured bone density to your body weight. The normal range is between 0.87 and 1.13; below that, bone density is low for your weight. Enter your weight and, from your DEXA report, the bone density of the lumbar spine (L1–L4), the hip (total) or both.
Manufacturer, usually shown in the footer of the graphics in the DEXA report.
Lumbar spine L1–L4
In the DEXA report usually “AP Spine”, row L1–L4.
Hip Total
Use the “Total” value, not a single region such as “Neck”.
| Site | Year | BMD (g/cm²) | B-score | DEXA scanner |
|---|---|---|---|---|
| Lumbar spine L1–L4 | ||||
| Hip Total |
For research purposes only: the B-score is not a recognised diagnostic criterion and does not replace a medical assessment. Your entries and the result are stored on our server without your name and evaluated statistically. © 2024 John van Limburg Stirum
Please enter the year of the DEXA measurement for the printout.
Please bring the printout with you to an appointment at the SGK.
How we investigate
We look for the causes. Osteoporosis can be the consequence of other disorders:
- Hormonal: Overactive parathyroid glands, Overactive thyroid, Cushing's syndrome, Lack of sex hormones
- Inflammatory: Rheumatoid arthritis, Inflammatory bowel disease, Chronic kidney failure
- Blood and tumours: Multiple myeloma
- Neurological: Immobility, Parkinson’s disease, After a stroke
- Functional: Loss of muscle (sarcopenia)
- Medikamente: Cortisone, Stomach protectants, Antidepressants, and others, see below
Diabetes mellitus, lupus erythematosus, coeliac disease, eating disorders such as anorexia nervosa or bulimia, and cancers with bone metastases can also increase the risk of osteoporosis.
Medication can also weaken the bone:
- Cortisone
- Antidepressants
- Stomach protectants (proton pump inhibitors)
- GnRH analogues
- Aromatase inhibitors
- Antidiabetic drugs (glitazones)
- Anti-epileptic drugs
- High-dose thyroid hormones
Laboratory tests in osteoporosis
Laboratory tests can follow the metabolism of the bone, which the density measurement does not show:
- Bone breakdown: CrossLaps in the blood, pyridinoline and deoxypyridinoline in the urine
- Bone formation: procollagen type 1 (P1NP) and bone-specific alkaline phosphatase (BSAP) in the blood
- New: calcium isotopes in the blood (the ratio of formation to breakdown)
Over countless measurements, pyridinoline and deoxypyridinoline in the urine have proven themselves as breakdown markers for bone collagen, particularly for checking the effect of micronutrients that support the bones.
Find out more: Bluttuning, preparing for the laboratory.
How we treat
Preventing fractures
A broken bone rarely has just one cause. Besides osteoporosis, what counts is the loss of mobility and balance, declining eyesight and reaction, loss of muscle and the risks a person takes. This is where we start:
- Improving mobility: exercise, hopping
- Strength training
- Avoid being underweight
- Enough protein, which includes good teeth and vigorous chewing
- Improving balance
- Optimising eyesight
- Training the ability to react
- Dietary supplements, but no calcium
The most common causes of fractures are age-related lack of exercise, muscle weakness and an unsteady gait. This is therefore where treatment begins: regular physical activity with light strength training strengthens the muscles, mobility and the ability to avoid danger. It pays off especially in old age: studies from the USA showed a marked increase in strength even in people over 80.
Sport: bone needs loading
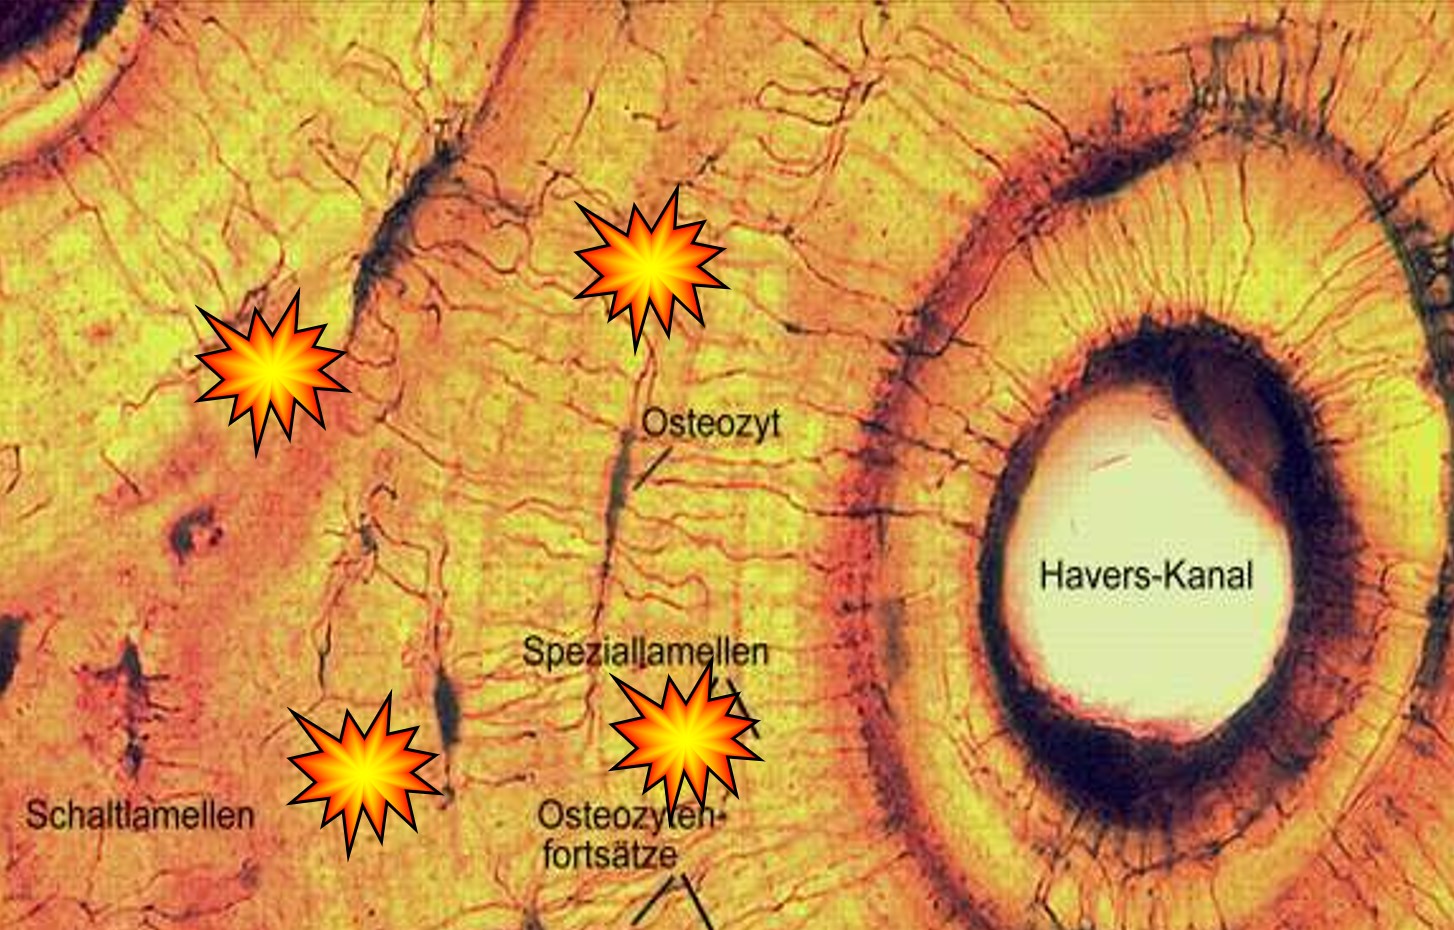
Mechanical loading is the decisive stimulus for building bone; without loading, bone is lost quickly. What matters is the force acting on the bone:
Bioelectric potentials
Bioelectric potentials play a fascinating role in bone metabolism, especially in bone healing and regeneration. These potentials are electrical signals generated by bone cells and involved in regulating bone growth and repair. They are based on the piezoelectric property of certain bone tissues, which generate electrical charges under mechanical load. These bioelectric signals promote the activity of the bone-forming cells and at the same time inhibit the activity of the bone-resorbing cells.
These exciting insights open up new possibilities for treating bone diseases and show how important regular physical activity is for maintaining a healthy bone structure.
Acid–base balance
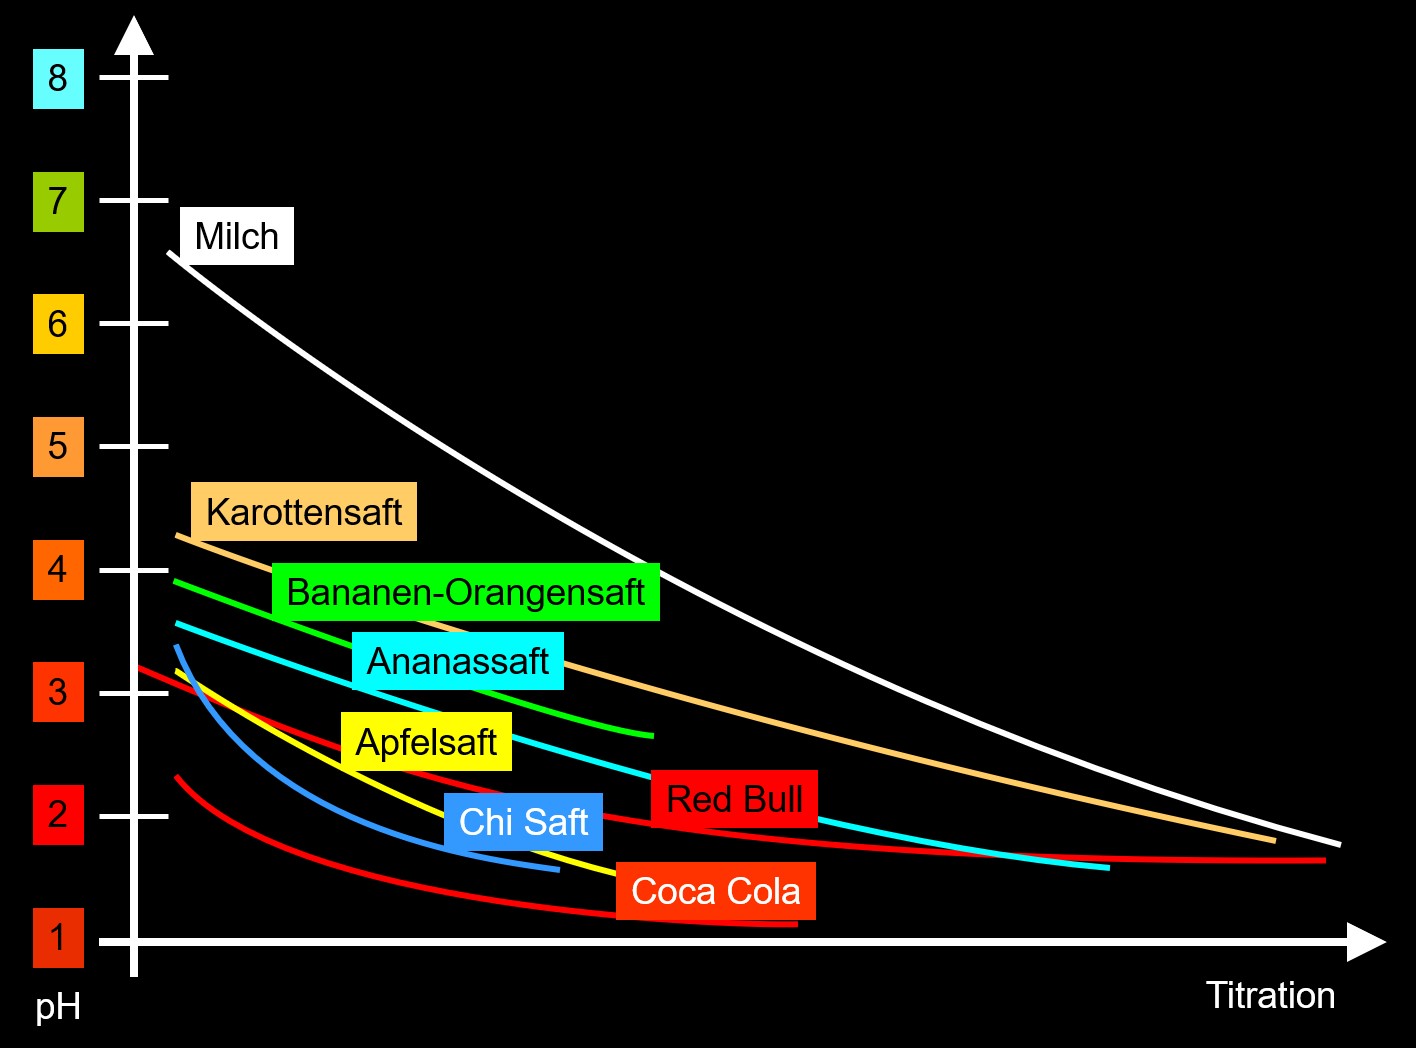
An alkaline environment activates the bone-building cells (osteoblasts) and promotes mineralisation. Acid inhibits formation and promotes breakdown. Balancing the bases is therefore part of the treatment.
Regular consumption of chemically acidic drinks such as cola or Red Bull can over-acidify the bones and thereby promote the development of osteoporosis.
Supporting new bone formation with nutrients
| Vitamins | What the bone needs them for |
|---|---|
| Vitamin K | Formation of new bone |
| Vitamin D | Incorporation of calcium |
| Folic acid | prevents the formation of homocysteine, which damages the bone |
| Vitamin B6 | lowers homocysteine, cross-links the collagen fibres |
| Vitamin B12 | lowers homocysteine |
| Vitamin C | a deficiency (scurvy) leads to osteoporosis |
| Minerals and trace elements | What the bone needs them for |
|---|---|
| Magnesium | activates vitamin D |
| Zinc | increases the activity of vitamin D |
| Boron | metabolism of vitamin D |
| Manganese | connective tissue of bone and mineralisation |
| Silicon | stabilises the collagen through cross-links |
| Copper | cross-links the collagen fibres |
| Molybdenum | component of metabolic enzymes |
| Others | What the bone needs them for |
|---|---|
| Potassium citrate | Base balance |
| Isoflavone | plant compound, binds to the oestrogen receptors of the bone cells |
Enough protein and collagen are part of this. From about the age of 55, or when taking stomach protectants, stomach acid is often lacking; protein and calcium are then absorbed less well.
For this we recommend OsteoStrength. It is available at Seegarten Klinik.
Calcium: not as a tablet
More lime does not mean more bone. In addition, calcium tablets carry risks: in a meta-analysis, pure calcium preparations increased the risk of heart attack by up to 30 per cent, especially at more than 800 milligrams a day (Bolland et al., British Medical Journal 2010). The German Society of Endocrinology states: “Calcium intake by tablet, if dosed above 500 mg/day, can result in kidney stones and vascular calcification” (2022).
Three to four dairy products a day: that is usually the recommendation of doctors and nutritionists. Milk is promoted above all for its high calcium content. In the discussion about milk and bone health, it is important to recognise that it is not so much the calcium but rather the protein and the alkaline character of milk that play the essential roles. Protein and an alkaline environment are fundamental for building and maintaining bone substance and thus stability. The alkaline character helps to maintain the acid–base balance, activates the bone-forming osteoblasts and thereby reduces the breakdown of bone substance.
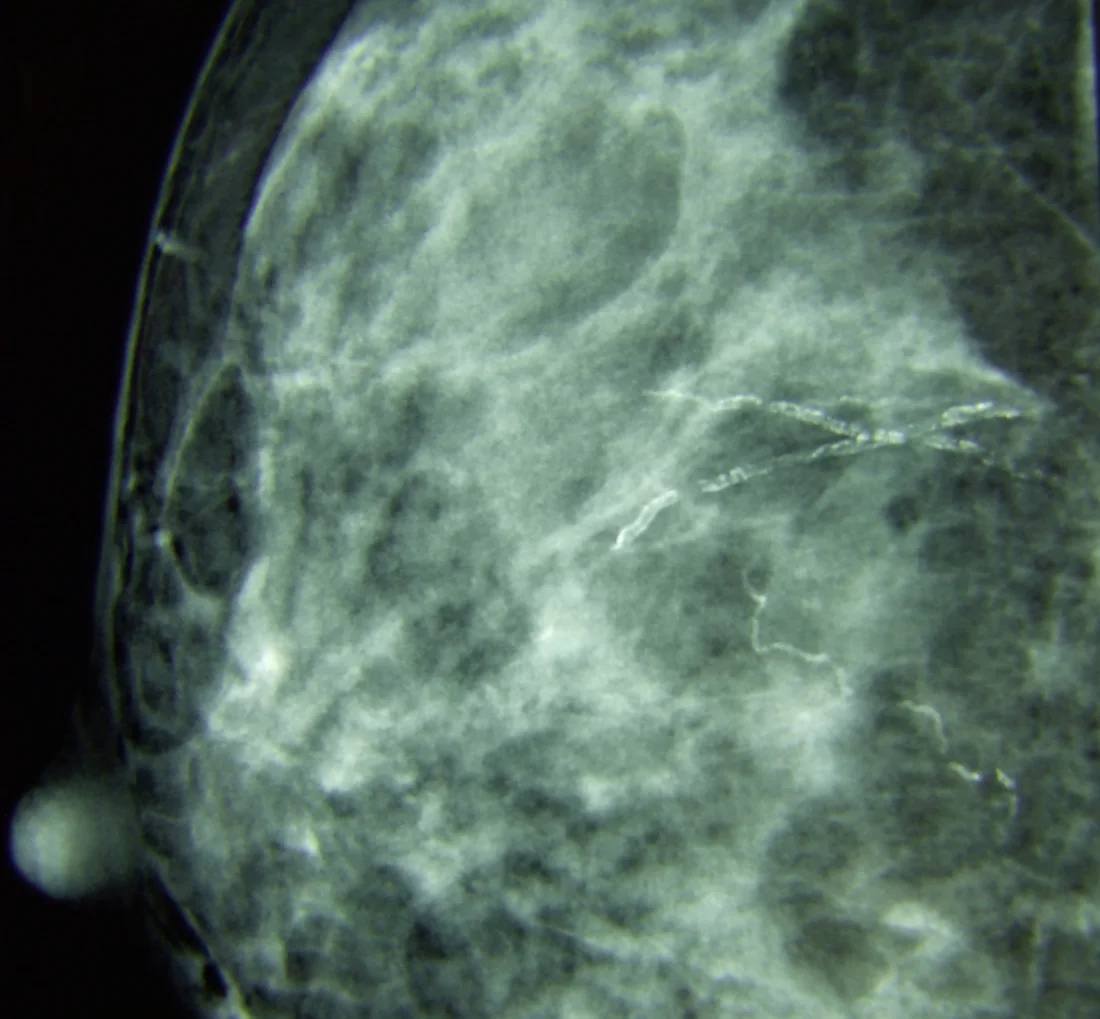
Patient study: vascular calcification after calcium supplements
Have you taken calcium supplements for more than 10 years and recently had a mammogram? Then you can send us these images. We will use them to assess your blood vessels.
Medikamente
Osteoporosis drugs work in two ways: they inhibit bone breakdown (bisphosphonates, denosumab, raloxifene) or stimulate formation (teriparatide, romosozumab). Whether a drug makes sense for you is something we discuss in the consultation, together with what you can do yourself.
Testosterone also contributes to bone health by promoting bone formation and reducing bone breakdown. In men, testosterone deficiency can lead to a loss of bone mass and an increased risk of osteoporosis. Testosterone replacement therapy can be used in men with low testosterone levels to increase bone mass and lower the risk of fracture.
Find out more: Sports Medicine for strength training, Endocrinology & Diabetology for hormones, acid-base balance.
A patient's case
This patient was 61 when she was faced with a diagnosis of osteoporosis. She was subsequently given bisphosphonates, drugs that inhibit bone breakdown. By 2009 a first success could be recorded on the basis of the bone density measurement. Because of side effects, she was switched to a preparation containing calcium and vitamin D. Two years later a decline in bone was recorded again. For this reason we changed the treatment to our special micronutrient therapy (free of side effects).
It can be seen quite clearly how bone density has increased steadily since then. Bone density was measured again in 2018. By then the patient was 73 (!) and showed a further increase in bone density of 15% within the last three years! The radiologist's comment: “I can't explain that.”
We can.
Background: the osteoporosis story
What osteoporosis is – and what it is not
Osteoporosis is a specific disease that must be clearly distinguished from the normal decrease in bone density in old age (so-called osteopenia). In the past, bones were described as osteoporotic only once fractures had occurred, usually of the spine, the hip or the wrist, as a result of disproportionately minor trauma. According to the newer definition, any decrease in bone mass is now osteoporosis, even if there are no fractures. With the ageing of the population, and with the lack of exercise and poor nutrition that come with modern life, osteoporosis is nevertheless becoming more and more apparent. Of course, this condition already existed in earlier times.
The “witches” who appear in history as old, stooped women confirm this observation. How many women were burnt as witches merely because they suffered from osteoporosis must remain an open question.
However widespread and well researched this change in the bones may be, there are major contradictions in the definition of the disease and therefore also in the recommended therapeutic measures. A selection follows:
In medical school, every student had to know precisely the difference between osteoporosis and so-called osteomalacia. The former consisted in a “wasting” of bone, the latter in a softening of bone. A wrong answer in the examination would have cost a good many marks. Nevertheless, clinical, pharmacological medicine practically equates osteoporosis with osteomalacia. Wherever the cause and treatment of osteoporosis are discussed, calcium deficiency is cited, and that is precisely what causes osteomalacia! In the student textbook of orthopaedics by Dr Alfred M. Debrunner, the development of bone in old age is (correctly) explained as follows: “While in the bone of a child the proportion of organic substances (collagen) is still relatively large and the bone is still flexible, in old age the inorganic proportion (calcium salts) increases steadily, and the bones become more rigid and more brittle.” According to the WHO, “osteoporosis is a disease characterised by low bone mass and deterioration of the fine structure of bone tissue, leading to increased bone fragility and ultimately to a higher risk of fracture”. There is no mention of calcium in the WHO documents either. We can therefore see at once that osteoporosis is not a calcium problem and is not solved by giving calcium.
Why calcium alone does not help
That bone formation in no way depends on “topping up” with calcium is shown by the following phenomenon: a cow gives 20–25 litres of milk twice a day. This contains around 1.2 g of calcium per litre, which corresponds to a daily calcium loss of 50 to 60 g. Yet, as a strict vegetarian, the cow consumes none of the “official” sources of calcium recommended for humans. This raises the awkward question: where does she get the lime from? The cow suffers neither from calcium deficiency nor from osteoporosis, although she gives the milk and does not drink it!
So what happens when the organism is offered calcium in “sufficient quantity”, as usual with vitamin D? The organism is then forced to incorporate the calcium. But since calcium can only be incorporated into an organic substance that is already there, and there is not enough of it in the bone, it has to be deposited somewhere else, for example in arteriosclerotic plaques of the aorta. Indeed, one comes across X-rays in which the calcium-laden aorta appears denser than the spine.
A lack of lime in childhood is rickets. It is usually caused by a lack of vitamin D, and lime alone does not cure it.
What bone density measurement measures
A further discrepancy arose with the introduction of bone density measurement (so-called densitometry). This procedure is supposed to detect osteoporosis and assess the success of a therapy. But once again the method misses the point. What interests us is the risk of a pathological fracture. Resistance to fracture, however, does not depend on the calcium content (and that is the only thing densitometry measures), but on elasticity. What we want in old age is youthful bones, “children's bones”. They are almost impossible to break.
Why? Because they are flexible and not yet calcified! If you put a child's bone into the densitometer, however, the result would inevitably be severe osteoporosis! The bones can hardly be made out. And of course this method can be used to “prove” that calcium therapy combats osteoporosis. Depositing lime merely simulates new bone formation, by calcifying trabeculae that were previously invisible on X-ray (because still cartilaginous and uncalcified). For fun, place a column of lime such as a stick of chalk in the X-ray beam and you will get a fantastic bone density. But … there is hardly anything more brittle!
Osteodensitometry is widely used nationally and internationally to diagnose osteoporosis, but it has been medically controversial for years. Since osteodensitometry was developed and came into use, expert opinions and statements have repeatedly been published in the scientific literature, at home and abroad, that call into question the validity and the benefit of this diagnostic method in part or even as a whole. It is known, for instance, that only some patients with increased bone fragility show low values in osteodensitometry, and conversely many patients with low values suffer no fractures. In other words, the relationship between the value measured by osteodensitometry and osteoporosis-related fractures that actually occur is not reliable. What is doubted above all is the use of the method to decide on preventive measures that have to be continued for many years, up to several decades. These include, for example, hormone replacement in women after the menopause, or the administration over years of other highly potent drugs that affect bone metabolism.
Summary report of the working committee “Medical Treatment” of the Federal Committee of Physicians and Health Insurance Funds on its deliberations in 1999 on the assessment of osteodensitometry under §135 para. 1 SGB V, 22 March 2000
Oestrogens
It is well known that women suffer from osteoporosis more often than men. And where is the little difference? Quite right! Up to the menopause, women have far more oestrogens than men. As long as women have oestrogens, they are said to be protected against osteoporosis. After the menopause, things go downhill. The entirely natural female postmenopause has been turned by Western medicine and the press into an oestrogen deficiency disease, and is a further expression of today's reductionism in medicine. Oestrogens are called for. But here we meet further contradictions. Bone loss has been found in women with so-called anovulatory cycles, which means that ovulation does not occur. In these women, however, it is not oestrogen that is lacking, but progesterone. Indeed, it has already been reported from the USA that giving progesterone alone increases bone mass. Oestrogens, at most, have a revitalising effect.
Oestrogens would have to be taken for about 20 years in order to maintain high bone density into old age. This medication is not free of side effects, however, since the risk of cancer of the womb or of the breast can rise. Nobody knows today whether the benefit really outweighs the harm.
Overweight women are fortunate. They produce oestrogens in their fatty tissue and are therefore immune to osteoporosis (according to the prevailing view in conventional medicine). Here again an explanation is attempted at the lowest level of medical knowledge. The fact is that osteoporosis is a very complex process with a still unmanageable number of unknown factors. But simple observation and trust in nature may help us here. At the latest since space travel it has been known that weightlessness can very quickly trigger osteoporosis. Mother Nature says to herself: why strong bones if I have nothing to carry? That is also why many slim patients show “osteoporosis” in the bone density measurement. Here they become victims of statistics (the person of normal weight is heavier). Overweight people depend on heavy, denser, stronger bones and for this reason show a “lower” risk of osteoporosis. In return, their bones also have to absorb more weight in a fall.
Osteoporosis campaigns
Again and again we are confronted with such campaigns. They are unmistakable sales instruments for drugs from the pharmaceutical industry. Approaches such as sport and nutrition are mentioned, but drug treatment always remains in the foreground, as a rule with the so-called bisphosphonates (a business worth billions, so-called “blockbusters”). These prevent bone breakdown, but in doing so they also cause the bone substance to become over-aged. Moreover, taking such medicines must not lull one into a false sense of security: “Nothing can happen to me now …”. Nutrition and sport, especially anti-gravity training as in a fitness club, remain the best conditions for bone health over many years.
So … at the next campaign, do not let yourself be talked into drug therapy too quickly. Always discuss the advantages and disadvantages, and especially the alternatives, with your family doctor.
Despite the many open questions and contradictions, it is possible for each individual to estimate their personal risk of osteoporosis and, with some motivation, starting as early as possible and persevering for years, to protect themselves against it.
“Puls” of 26 February 2018: problems with Prolia
Watch the programme on SRF (in German)
Comment by Dr. med. John van Limburg Stirum
The programme speaks of a “rebound effect”. It is surprising that the scientists are astonished by this phenomenon. It is known of all biological systems that any suppression of a natural function is followed by a counter-reaction. Walking barefoot in the snow is one example: afterwards the feet are hot! This phenomenon does not occur, however, when poisoning is involved, as with the bisphosphonates that inhibit bone breakdown. The recommendation of conventional medicine to taper off the therapy with bisphosphonates after stopping denosumab (Prolia, a monoclonal antibody) is therefore remarkable. In other words: first suppression, then poisoning.
Fortunately, there are natural remedies and procedures which, by contrast, promote the building of bone and may thus be an alternative to the standard therapy.
Advertisement for an osteoporosis drug – August 2019

A provocative question …
Which bridge would better survive an earthquake?